
Mental illness doesn’t cancel your right to refuse treatment
 adminUpdated 1 hour Ago5 Mins read
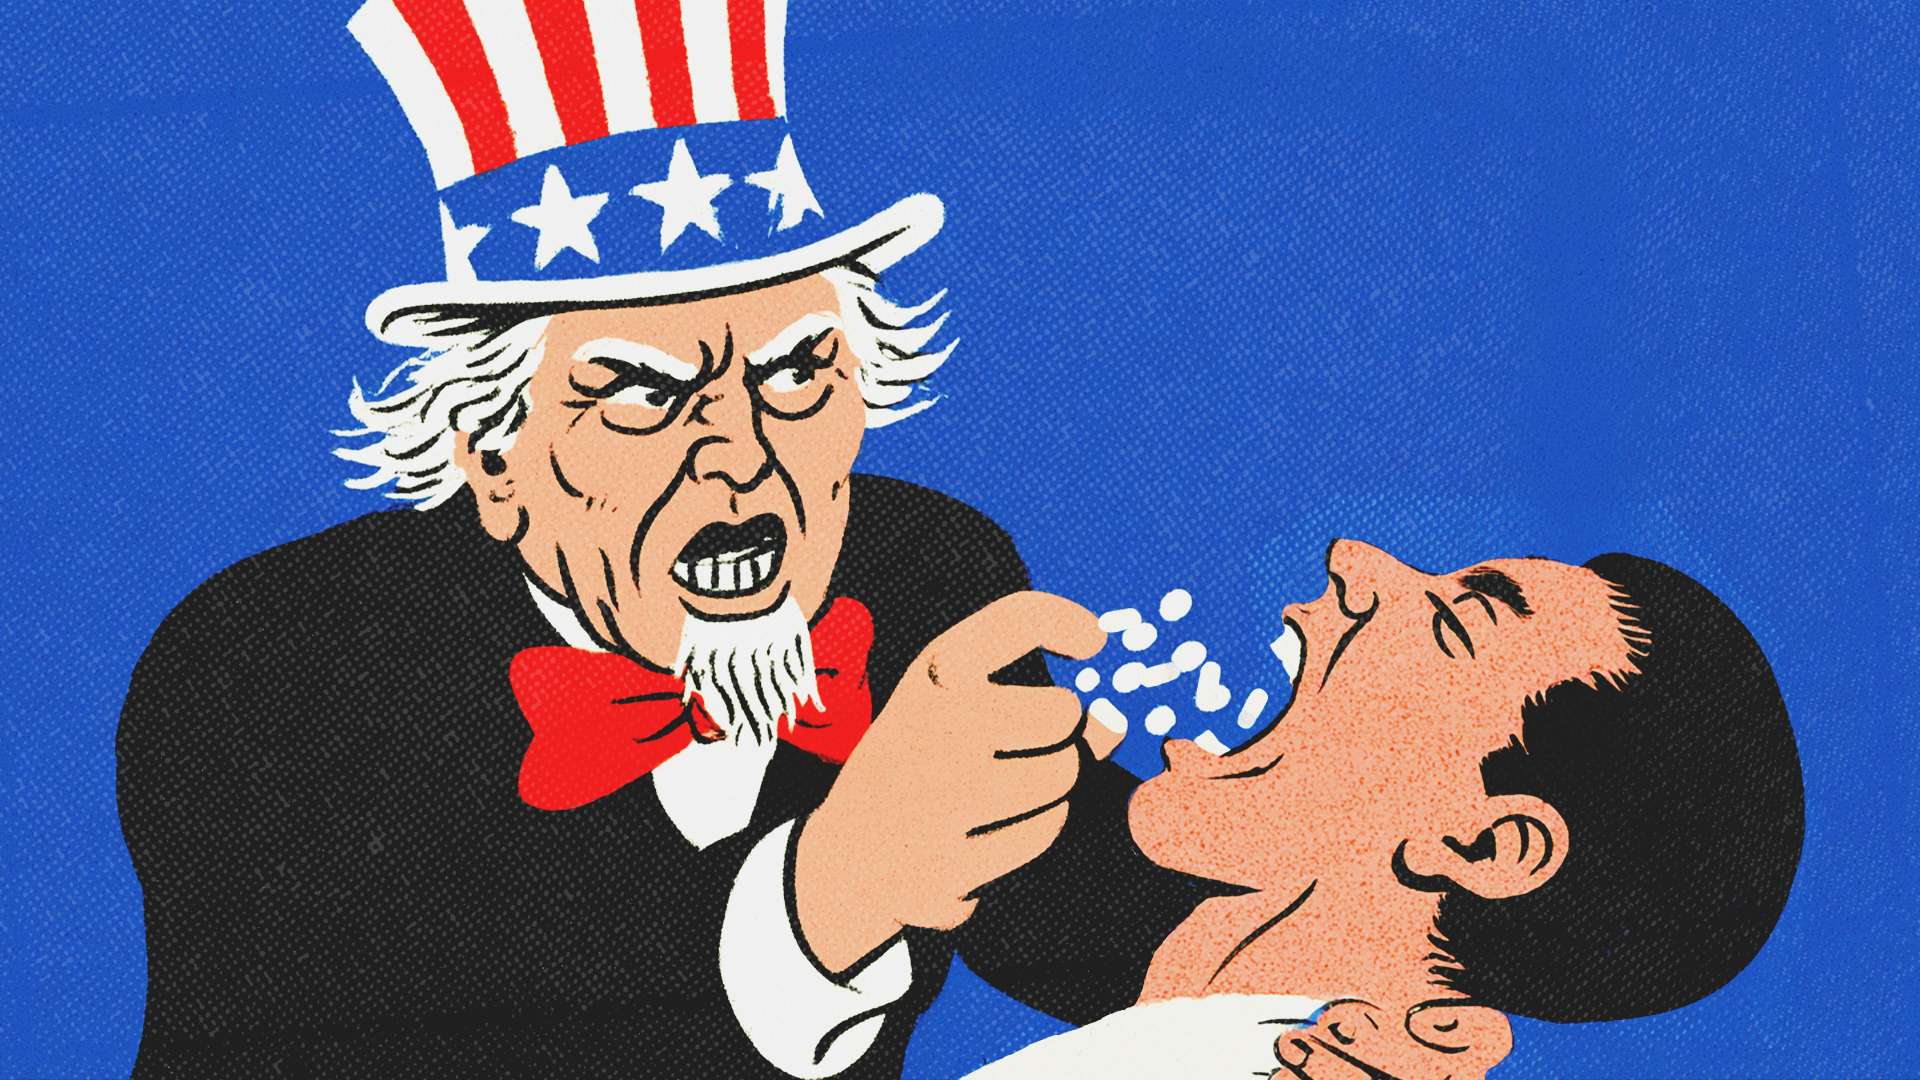
If a treatment can improve your health, does that give the government the right to force it onto you? Should the state compel people with diabetes to take insulin, patients with hypertension to take their medications, or people with obesity to lose weight?
Most Americans would recoil at such proposals. Yet when it comes to people diagnosed with psychiatric disorders, many people seem willing to make an exception.
A physician who administers treatment to a competent adult against the patient’s will violates one of medicine’s most fundamental ethical principles: informed consent. Why should that principle carry less weight when the doctor is a psychiatrist? Yet in a recent City Journal article, Stephen Eide and Valerie Franchitti of the Manhattan Institute argue that public support for involuntary psychiatric treatment reflects a welcome recognition of its potential benefits.
Strangely, the article entirely avoids the concept of informed consent. Where it acknowledges any limitations to involuntary treatment at all, it considers only the possibility that coercive treatment may increase stigma against mental illness.
But the more fundamental objection is liberty. A psychiatric diagnosis does not extinguish your right to control your body. Competent adults have the right to decide what substances they consume, which medical treatments they accept, and what risks they take, even when others consider their choices unwise or self-destructive. As the psychiatrist Thomas Szasz wrote in 1997, “I oppose involuntary psychiatric interventions not because I believe that they are necessarily ‘bad’ for patients but because I oppose using the coercive apparatus of the state to impose psychiatric relations on persons against their will.”
Eide and Franchitti write, “The public is right to suspect that involuntary treatment can be effective.” They cite data from the New York State Office of Mental Health showing substantial reductions in hospitalization, incarceration, homelessness, substance abuse, and suicide attempts following enrollment under Kendra’s Law, which mandates outpatient psychiatric treatment. Yet these data do not establish that coercion caused those improvements. Participants also received increased access to psychiatric services, case management, and other support. Without adequately separating the effects of those services from the effects of coercion itself, the reported improvements cannot establish that compulsory treatment was responsible.
The authors also justify involuntary psychiatric treatment by citing subway attacks, mass shootings, and other violent incidents. But there is a fundamental difference between holding people accountable for violating others’ rights and confining them because they might become dangerous. Communities can enforce laws against assault, trespassing, and public nuisance without criminalizing homelessness or mental illness.
Moreover, involuntary commitment to a psychiatric hospital or rehabilitation facility—sometimes for prolonged periods—deprives people of their liberty without a criminal conviction. Although civil commitment involves judicial procedures and opportunities for review, continued confinement may depend heavily on mental health professionals’ assessments of whether patients meet release criteria. As Szasz warned, coercive psychiatrists can thus function as “judges and jailers not physicians and healers.”
Severe mental illness can impair decision-making, sometimes profoundly, but diagnosis and incapacity are not the same. Even among psychiatric inpatients housed for severe mental illness, a meta-review of the research at BMC Psychiatry shows, most retain the capacity to make treatment decisions. Outside of hospitalized patients, decision-making capacity is even higher.
The legal scholar Elyn Saks, who has lived with schizophrenia, brings both personal experience and academic expertise to the debate over involuntary psychiatric treatment. Having experienced involuntary hospitalization, physical restraints, and forced medication, Saks has questioned the assumption that mental illness justifies overriding patients’ wishes. In her book Refusing Care she examines the ethical and legal problems posed by involuntary hospitalization, forced medication, and physical restraints. Saks and the psychiatrist Dilip Jeste have also reviewed empirical research on decision-making capacity among people with psychiatric and substance use disorders, analyzing how capacity varies among individuals and how clinicians can assess and enhance patients’ ability to make informed decisions.
Though the medical field has developed structured interviews with standardized scores for mental incapacity, doctors can disagree on assessment. Mental capacity is also decision-specific and time-specific, not a permanent status attached to a diagnosis. That same BMC Psychiatry review of the literature describes the impairments seen in psychosis as “temporal, identifiable, and responsive to interventions,” such as presenting information in simpler terms.
Even when incapacity can be established, we must adhere to the principle of least restrictive intervention. Any intervention must be justified by the circumstances, limited to what is necessary, and designed to preserve as much individual freedom as possible. Compulsory treatment takes different forms, each imposing distinct restrictions on individual liberty. Assisted outpatient treatment allows people to remain in the community but subjects them to a court order governing treatment. Involuntary inpatient commitment deprives people of their physical liberty through hospitalization, while forced medication goes further by overriding bodily autonomy. So impaired decision-making capacity does not automatically justify confinement, let alone forced medication.
Medication can reduce psychotic symptoms, and some psychiatric patients who initially refuse treatment later believe it helped them. But evidence that medication works is not the same as evidence that compulsion produces better outcomes than voluntary treatment, particularly when a person’s decision-making capacity may improve as an acute episode subsides.
In 2024, a scoping review in the journal Psychiatry, Psychology and Law found mixed evidence of benefits and harms from involuntary inpatient treatment. Patients admitted involuntarily often experienced improvements in symptoms and functioning, but they also tended to enter treatment with more severe illness, making it difficult to determine how much of the improvement resulted from compulsory intervention itself. Involuntary admission was also associated with higher financial costs and worse patient experiences, including feelings of coercion, loss of freedom, and lower satisfaction. In 2018, The Canadian Journal of Psychiatry published a systematic review of coercive measures; it found that patient experiences were predominantly negative and frequently involved adverse consequences. Overall, no consistent evidence shows that involuntary treatment itself causally improves outcomes, although it unquestionably restricts patients’ freedom and imposes costs on taxpayers.
These concerns are compounded by a health care system that financially incentivizes psychiatric overdiagnosis and overmedication, regardless of whether additional interventions yield commensurate benefits for patients.
The difficult case arises when a person genuinely cannot reason about treatment options or communicate an informed choice, and when delaying intervention creates an immediate risk of harm. In such cases, the ethical principle should be the same as elsewhere in medicine: Temporary treatment may be justified when informed consent cannot be obtained, using an advance directive or surrogate when available, and only to the minimal extent necessary to manage the emergency and restore the patient’s ability to decide. A credible, imminent threat to another person presents a separate public-safety justification for state intervention. But even support for those types of emergency interventions is not the same as support for broad, long-term involuntary psychiatric treatment based on supposed mental incapacity.
City Journal frequently advocates free markets, individual liberty, and limits on government intervention. Yet these writers appear willing to grant the state considerable authority over people’s medical decisions without adequately distinguishing those who lack decision-making capacity from those who retain it. If we distrust government officials to make economic decisions for us, why should we trust them to make decisions about our bodies and medical care?






Leave a comment